

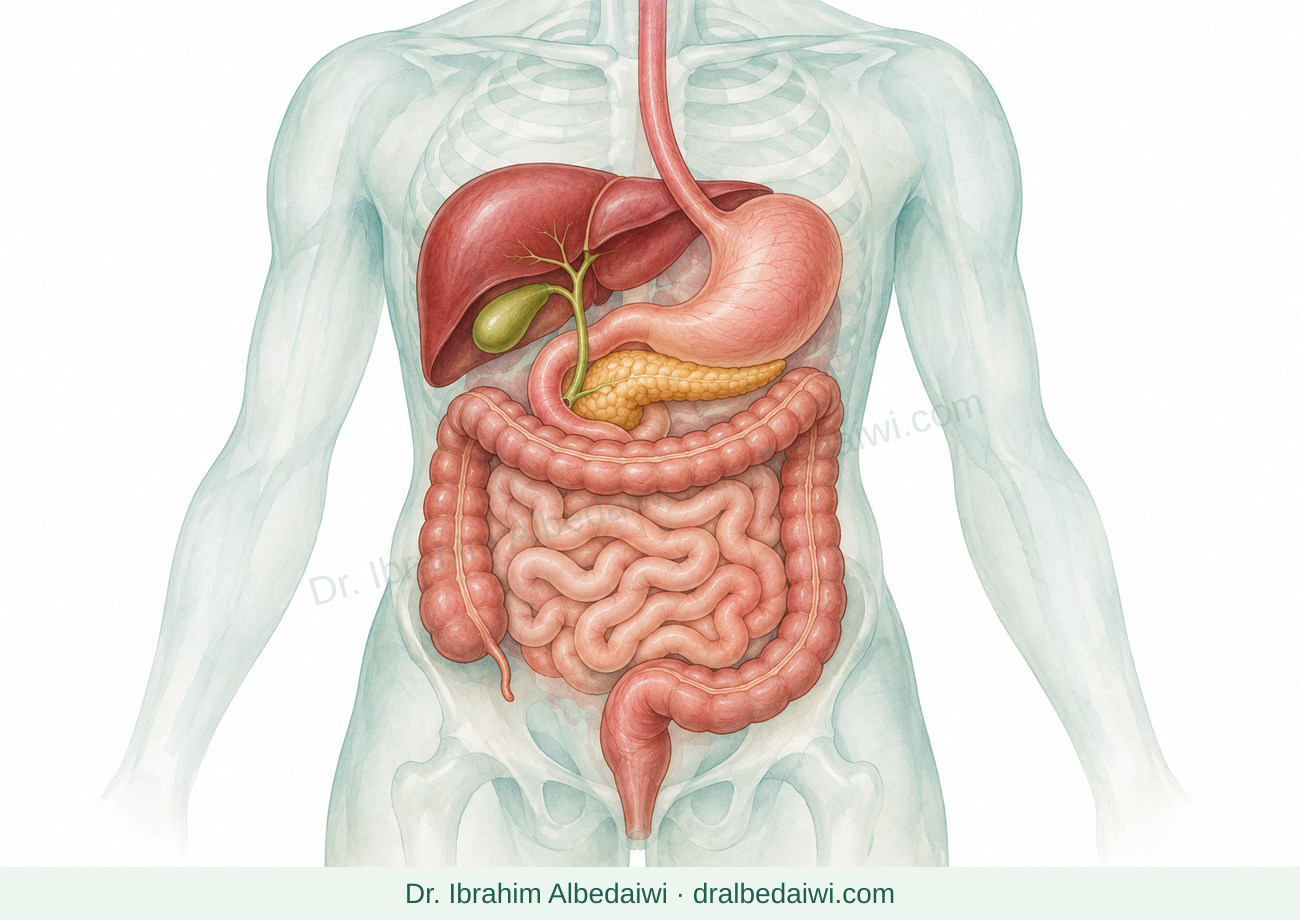

Hepatitis C
Content date: 14 November 2026
Most people can be cured with oral medicines. An HCV RNA test checks for active virus in the blood; a repeat test after treatment confirms cure.
Your next step
Confirm your post-treatment test-of-cure appointment; antibodies alone do not establish active infection.
Get urgent help: Vomiting blood, black, tarry stools even without dizziness, new confusion, or severe jaundice with general deterioration.
What is hepatitis C?
- This is an infection with a virus that reaches the liver through blood and can remain there, causing inflammation that may persist for years. Some people clear a new infection naturally, but persistent virus may lead to chronic infection. Liver scars can develop over time and progress to cirrhosis in some patients.
- Many people have no symptoms, and infection may be found incidentally. Symptoms, if present, may include tiredness, nausea, mild upper abdominal pain or jaundice. These are not specific to hepatitis C, and their absence does not exclude infection or damage.
What is the difference between treating the virus and its effects?
- Modern tablets target steps in viral replication until the virus is eliminated from the body. Cure means the viral test remains negative at the specified time after treatment, not simply improved liver enzymes. Antibodies may remain positive because they record the body’s previous exposure.
- After cure, liver injury falls and fibrosis may regress over time. Cirrhosis (F4) can also improve, but this does not guarantee a normal liver or remove the need for follow-up. Assessment before treatment guides care after cure; do not stop attending when tablets finish. Cure does not prevent a new infection after exposure to infected blood.
The hepatitis C treatment journey
Antibody test
May show past exposure; it does not prove active infection on its own.
HCV RNA test
Identifies the virus. Tests and interactions are reviewed before treatment.
Prescribed treatment
Daily tablets on your plan. Do not stop just because you feel better.
Confirm cure
HCV RNA testing at least 12 weeks after treatment finishes.
Cure does not prevent reinfection. People with established cirrhosis continue liver and cancer surveillance on their clinician’s plan.
© 2026 Dr. Ibrahim Albedaiwi · Patient GuideAntibodies or the virus itself?
- An antibody test shows previous exposure and may remain positive after cure. A viral RNA test identifies active infection.
- If the viral test result has not been issued, we cannot treat it as negative or use it to confirm cure.
- If you may have been exposed within the past six months, or have a weakened immune system, your doctor may request HCV RNA even when the antibody test is negative. A very early test can be negative before infection becomes detectable; tell the team when exposure occurred and follow the repeat-testing plan.
Before treatment
- We assess scarring and liver and kidney function, and review hepatitis B and HIV tests and drug interactions; coinfections can affect treatment and follow-up.
- Bring a list of all medicines and supplements, particularly medicines for acidity, cholesterol, heart conditions or epilepsy. Tell the team about pregnancy or plans for pregnancy.
What is treatment like?
- Usually daily tablets for 8–12 weeks, although duration varies in some situations. With adherence, these treatments cure more than 95% of suitable patients.
- In our clinic, a usual first choice for suitable patients is sofosbuvir plus daclatasvir once daily for 12 weeks, particularly if previously untreated and without cirrhosis. Cirrhosis or previous treatment failure may require a different regimen or duration. The linked medicine card explains use, monitoring and precautions.
- Sofosbuvir/velpatasvir or glecaprevir/pibrentasvir are also standard options for eligible patients. The team considers liver disease stage, prior treatment, drug interactions and availability.
- Take doses as prescribed and do not stop because symptoms improve. If you miss a dose or start a new medicine, ask your pharmacist or team for instructions specific to your treatment.
When can I say I am cured?
- We usually request a viral test 12 weeks or more after treatment ends to confirm the virus remains undetectable. An undetectable virus during treatment alone does not establish a lasting cure.
- If cirrhosis (stage 4 scarring, F4) was established before treatment, liver cancer surveillance usually continues every 6 months after cure. Do not stop it because liver enzymes or a stiffness measurement improve; your specialist reviews the follow-up plan.
Protecting yourself and others
- Transmission is mainly through blood. Do not share shaving equipment, toothbrushes or needles, and do not donate blood. It does not spread through hugs or ordinary food sharing.
- Cure does not provide immunity to a new infection, and there is no hepatitis C vaccine. Discuss hepatitis A and B vaccines if you are not immune.
- Avoid alcohol and unknown supplements, maintain a healthy weight and manage blood glucose; curing the virus does not prevent other liver diseases.
If exposure risk continues after cure
- Ask about repeat HCV RNA testing, usually annually when exposure risk continues. The antibody may remain positive after cure and cannot by itself identify reinfection.
Pregnancy, breastfeeding and your baby’s test
- If you are planning pregnancy, discuss treating hepatitis C beforehand where possible. If infection is present during pregnancy, coordinate follow-up and treatment with your liver and maternity teams; do not change medicine yourself.
- If infection was present during pregnancy, tell your baby’s doctor and arrange testing even if the baby appears well. CDC recommends HCV RNA testing for exposed infants at age 2–6 months; the pediatrician determines the appropriate local plan and what to do if that window was missed.
- Hepatitis C alone does not usually prevent breastfeeding. Temporarily stop feeding from a breast with a cracked or bleeding nipple and seek advice. Maternal medicines and any coinfection, such as HIV, require a separate review.
When to get help
Vomiting blood, black, tarry stools even without dizziness, new confusion, or severe jaundice with general deterioration.
Difficulty obtaining or completing medicine, starting a new medicine, or abdominal swelling and new jaundice.
Guides for your care journey
Read the related guides together:
Related guides
Sofosbuvir + daclatasvir for hepatitis C
Sofosbuvir/velpatasvir for hepatitis C
Glecaprevir/pibrentasvir for hepatitis C
Ledipasvir/sofosbuvir for hepatitis C
Sofosbuvir/velpatasvir/voxilaprevir (Vosevi) for hepatitis C
Sources
AASLD/IDSA: Treatment monitoring
AASLD/IDSA HCV Guidance monitoring · current accessed 2026-11-08
SASLT: hepatitis C treatment guideline (2024)
Saudi MOH: viral hepatitis patient information (accessed 10 November 2026)
AASLD: regression of fibrosis and cirrhosis (2026)
Clinical source · hcvguidelines.org
Clinical source · hcvguidelines.org